Thursday, 14 October 2010

MRCP revision battle 29.1: Hypoglycaemia

After nearly a week away I'm back with a bumper set of battles, the first of which is hypoglycaemia, which has been a recurring theme in both my patients and myself this week!  Enjoy!


MRCP revision battle 29.1: Hypoglycaemia
MRCP revision battle 29.2: Thyroid eye disease
MRCP revision battle 29.3: Hyperlipidaemia
MRCP revision battle 29.4: Lipid-lowering treatment
MRCP revision battle 29.5: Restless legs syndrome
MRCP revision battle 29.6: Histocytosis X
MRCP revision battle 29.7: Bartter's Syndrome
MRCP revision battle 29.8: Gitelman Syndrome
MRCP revision battle 29.9: Liddle's Syndrome


MRCP revision battle 29.1: Hypoglycaemia


Hypoglycaemia is defined as plasma glucose <3mmol/l.


In general in diabetics autonomic symptoms of hypoglycaemia (sweating, anxiety, tremor, palpitations) occur below 3.5mmol and neurological symptoms (confusion, drowsiness, seizures, coma) occur below 2.5mmol.

If a diabetic has frequent hypos they may become 'insensitive' and no longer experience symptoms before becoming unresponsive.  Symptoms may be 'restored' by carefully avoiding hypos for 3 months.


Causes of hypoglycaemia are easy to remember as it "IS PLAIN" to see...
  • Insulin
  • Sulphonyureas/other drugs
  • Pituitary insufficiency
  • Liver failure
  • Addisons disease or alcohol
  • Insulinoma
  • Neoplasms eg retroperitoneal fibrosarcomas than secrete IGF

Take bloods for glucose, insulin, c-peptide and plasma ketones.
Normal/high insulin, no ketones: insulinoma, drugs
Insulin low, no ketones: non-pancreatic neoplasm
Insulin low, ketones high: alcohol, addissons, pituitary insufficiency.


Post-pradial hypoglycaemia can occur post-gastrectomy


Whipples Triad is a set of criteria which if fulfilled suggest a patient's symptoms are due to hypoglycaemia:
  • symptoms suggestive of hypoglycaemia
  • BM < or equal to 2.5
  • symptoms relieved by food.

Treatment

I'm sure this is all old-hat to you all... get the pt to eat if they can, 1mg IM glucagon if they can't and no IV access (remember glucagon effects only last for 20 mins and may not work at all in alcoholics) and if IV is an option the 50mls of 50% glucose or the more modern 200mls of 10% (less abrasive to the veins)


Now for some TED time...

MRCP revision battle 29.2: Thyroid eye disease

Thyroid eye disease, referred to by its friends as 'TED', can occur in people who are hyperthyroid, hypothyroid or euthyroid.


Thyrotoxicosis from any cause can cause lid lag and lid retraction.


However, only Graves disease causes:
  • periorbital oedema
  • conjunctivial injection
  • proptosis/exophthalmos
  • opthalmoplegia/diplopia
  • papilloedema

(as an aside, I've always been mystified by the difference between proptosis and exophthalmos.  Unfortunately it appears I'm not the only one as some sources suggest the difference is related to the degree of protrusion whilst others say exophthalmos is used if the aetiology is endocrine and proptosis is used if the aetiology is not endocrine...)


25-50% of patients with Grave's disease have TED.


Risk of TED is increased in smokers.


The danger of TED is optic nerve compression.  Symptoms/signs of optic nerve compression include:
  • blurred vision/decrease VA
  • decreased colour vision
  • a relative afferent papillary defect


Treatment for TED is topical lubricants, steroids if severe and possibly even surgery.


Now for a horrid battle with hyperlipidaemia...

MRCP revision battle 29.3: Hyperlipidaemia

This battle is quickly going to get complex and aims only to be an MRCP-focused overview rather than a comprehensive discussion.  It is divided into 5 stages:
  1. The basics
  2. Hypercholesterolaemia
  3. HDL - the good cholesterol
  4. Hypertriglyceridaemia
  5. Mixed


1. The Basics

Hyperlipidaemia = raised lipids.  Lipids come in 4 main 'flavours':

  1. chylomicrons = carry triglyceride
  2. LDL = mainly cholesterol (50%, 10% TG) = the 'bad' flavour
  3. HDL = mainly phospholipid = the 'good' flavour, carry cholesterol back to the liver
  4. VLDL = mainly triglyceride (60%, 20% cholesterol)

Signs:
  • corneal arcus = grey-white ring around cornea
  • xanthelasma = yellow collection of cholesterol under skin
  • xanthomata = 'lumps' of cholesterol
  • eruptive xanthomata = small yellow-orange papules that appear all over body
  • lipaemia retinalis = 'creamy' appearence of blood vessels on fundoscopy

So lets look first at cholesterol and hypercholesterolaemia.


2. Hypercholesterolamia

a. Familial
  • LDL receptor dysfunction
    • cholesterol 7.5-16
    • raised LDL
    • tendon xanthomata, corneal arcus and xanthelasma
    • heterozygous prevalance 1/500 --> MI in 40s
    • homozygous --> MI in 20s
  • Polygenic hypercholesterolaemia
    • cholesterol 6.5-9
    • raised LDL
    • xanthelasma and corneal arcus

 b. Acquired
  • nephrotic syndrome
  • renal transplant
  • cholestasis
  • hypothyroidism


3.  HDL

HDL is 'good' cholesterol

It is higher in:
  • thin people
  • exercise
  • oestrogens
  • alcohol
  • low triglycerides

It is lower in:
  • obesity
  • sedentary states
  • post-puberty males
  • smoking


4. Hypertriglyceridaemia

a. Familial
  • failure to metabolise chylomicrcons
  • features include:
    • eruptive xanthomata
    • lipaemia retinalis
    • retinal vein thrombosis
    • pancreatitis
    • hepatosplenomegaly

b. Secondary
  • diabetes
  • obestiy
  • alcohol
  • chronic renal failure
  • liver disease
  • drugs such as thiazides, beta blockers or oestrogens


5. Mixed hyperlipidaemia
  • Look for palar xanthomas and tuberous xanthomas


After that wordy and depressing battle, lets move on to treatment of hyperlipidaemia...

MRCP revision battle 29.4: Lipid-lowering treatment

NICE recommends that all those with a 10 yr cardiovascular risk of >20% should be offered lipid-lowering therapy.

1st line: 40mg simvastatin
Measure LFTs when starting, at 3 months and at 12 months.


In primary prevention there is no 'target' cholesterol
In secondary prevention the target is less than 4mmol/l cholesterol and less than 2mmol/l LDL


If statins are not tolerated consider:
  • fibrates
  • ezetimibe
  • nicotinic acid


Mechanisms of action


Statins are HMG CoA reductase inhibitors.  They therefore work by decreasing the production of cholesterol in the liver.  The decreased production of cholesterol in the liver also results in the liver absorbing and processing more LDL, hence further reducing cholesterol.


Grapefruit juice decreases the metabolism of statins.  Patients on statins are therefore advised to avoid grapefruit juice as it would increase the risk of the rare side effect of rhabdomyolysis


Ezetimibe works by preventing intestinal absorption of cholesterol.


Fibrates are PPAR alpha receptor agonists.  They therefore increase clearance of VLDL and remnant particles and decrease TG secreation.

Fibrates and statins tend not to be used together due to increased risk of rhabdomyolysis.


Nicotinic acid (=vitamin B3) blocks breakdown of fats in adipose tissue. 
It can cause facial flushing.


For the really keen:
NICE lipid modification guide

After those heavy-going battles lets tackle something light - restless legs syndrome...                             

MRCP revision battle 29.5: Restless legs syndrome

Restless legs syndrome, sometimes known as Ekbom's syndrome, is a condition in which a person has unpleasant sensations in their legs and a desire to move them.


Restless legs may be idiopathic or secondary to:
  • pregnancy
  • iron deficiency
  • ureamia
  • diabetes
  • RA

1st line treatments are dopamine agonists such as pramipexole
2nd line treatments include benzodiazepines or gabapentin.


To keep the neurones jumping lets move on to a completely different topic again - histiocytosis X...

MRCP revision battle 29.6: Histiocytosis X

Histocytosis X, aka Langerhans-cell histiocytosis, is a group of disorders in which there is organ infiltration by granulomatous lesions containing clonally proliferated dendrintic (=Langerhams) cells.


The most commonly affected organs are lungs and bones.


Lung histiocytosis tends to affect young adults and is commonest in smokers.

The CXR shows multiple ring shadows with diffuse reticulo-nodular opacities affecting mainly the upper and mid zones.


Biopsy would show characteristic Birbeck granules.


Treatment is ?local excision, ?steroids.


Now onwards for a run of the last 3 short battles of the day, starting with Bartter's Syndrome...

MRCP revision battle 29.7: Bartter's Syndrome

Bartter's Syndrome is an autosomal recessive condition in which there is defective chloride reabsorption in the Na-K-2Cl channels in the loop of Henle resulting in severe hypokalaemia.


It presents in childhood with failure to thrive and polyuria/polydipsia


Blood pressure is normal/low.

There is hyperreninaemia and hypertrophy of the JGA.


Treatment is with potassium replacement and NSAIDs.


Next... Gitelman Syndrome....

MRCP revision battle 29.8: Gitelman Syndrome

Gitelman Syndrome is an autosomal recessive disorder in which there is decreased salt reabsorption in the distal tubule resulting in hypokalaemia due to secondary hyperaldosteronism.


Patients with Gitelman Syndrome have:
  • metabolic alkalosis
  • low potassium
  • low magnesium
  • usually normal blood pressure

Treatment is magnesium and potassium replacement.


Finally - Liddles!

MRCP revision battle 29.9: Liddle's Syndrome

Liddle's syndrome is an autosomal dominant condition caused by enhanced sodium reabsorption in the DCT.

It results in:
  • hypertension
  • hypokalaemia
  • metabolic alkalosis

Treatment is salt restriction, potassium, amiloride.

Saturday, 9 October 2010

MRCP revision battle 28.1: Haemochromatosis

I feel like I'm possibly starting to make some inroads into this MRCP revision thing, and my chocolate dependency level has decreased a little.  Today is another random assortment of gems:


MRCP revision battle 28.1: Haemochromatosis
MRCP revision battle 28.2: Syphilis
MRCP revision battle 28.3: Third nerve palsy
MRCP revision battle 28.4: G6PD deficiency
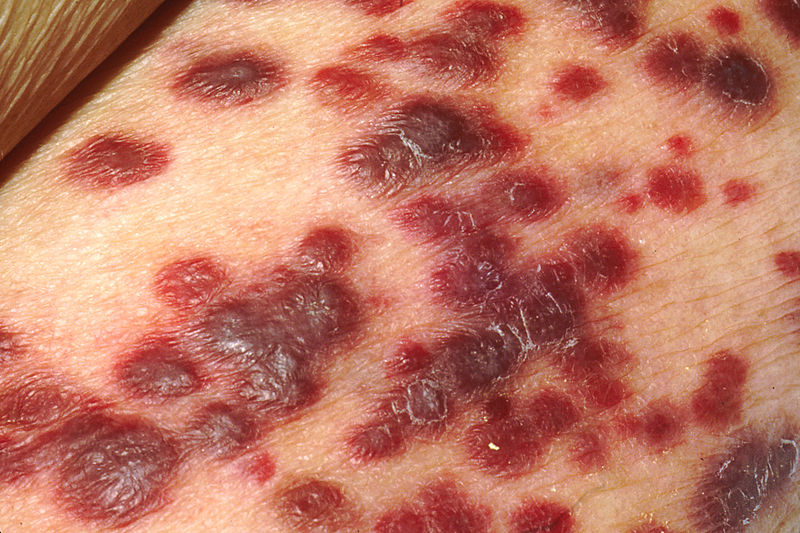
MRCP revision battle 28.5: Kaposi's sarcoma
MRCP revision battle 28.6: Chronic Myeloid Leukaemia
MRCP revision battle 28.7: Gerstmann's Syndrome


MRCP revision battle 28.1: Haemochromatosis


Haemochromatosis is an excessive accumulation of iron.
There is increased intestinal absorption leading to deposition in joints, skin, the heart, liver, pancreas, adrenals and pituitary.


It is an autosomal recessive disorder, inherited on chromosome 6.


Presentation is initially with tiredness and arthralgia

Later problems include:
  • diabetes mellitus (bronze diabetes)
  • slate-grey skin
  • liver disease/cirrhosis
  • cardiac failure/cardiomegaly
  • pseudogout
  • hypopituitism
  • >30% develop hepatocellular carcinoma


Males are affected earlier and more severely than females.


Diagnosis is by:
  • transferrin saturation >50%
  • ferritin >300-500micrograms/l (depending on guidelines)
  • liver biopsy  - Perls stain to show hepatic iron >180micromol/g


Treatment is regular venesection and ?chelation with desferrioxamine


Haemosiderosis is secondary haemochromatosis.  


Causes of haemosiderosis include:
  • beta thalassemia
  • sideroblastic anaemia
  • aplastic anaemia
  • transfusions
  • alcoholic cirrhosis
  • chronic viral hepatitis
  • porphyria cutanea tarda


Thats enough iron for one day... onwards to some syphilis...

MRCP revision battle 28.2: Syphillis

Syphilis is another of those conditions which is a common differential in MRCP questions.


Syphilis is caused by the spirochaete treponema pallidum.


There are 4 stages of syphilis:


1) Primary
  • painless genital ulcer
  • known as a chancre
  • highly infectious


2) Secondary
  • occurs 4-8 weeks after the chancre
  • rash, malaise, lymphadenopathy, temperature
  • condylomata lata


3) Tertiary syphilis
  • >2yrs after secondary
  • gummas (=granulomas) form in skin, mucosa and viscera


4) Quaternary syphilis
  • cardiovascular
    • aortic aneurysm
    • aortic regurgitation
  • neurosyphilis
    • cranial nerve palsies
    • general paralysis of the insane
    • tabes dorsalis
      • sensory ataxia
      • numb legs
      • lightening pains
      • upgoing plantars
      • argyll robertson pupil


Tests:
  • cardiolipin antibody = VDRL, RPR
    • not syphilis specific
    • insensitive in late syphillis
    • becomes negative after treatment
    • false +ives in pregnancy, SLE, TB, leprosy, malaria, HIV
  • treponeme-specific antibody = TPHA
    • remains positive after treatment
  • dark ground microscopy


Treatment:
  • IM penicillin or PO doxcycline


Random eponymous warning - Jarisch-Herxheimer reaction:
  • raised pulse, temp and vasodilation
  • occurs hours after 1st dose of antibiotics
  • due to release of endotoxin
Occurs in around 90% of patients with secondary syphilis.


Now on for a bit of third nerve palsy....

MRCP revision battle 28.3: Third nerve palsy

Cranial nerve III = oculomotor nerve arises in the rostral midbrain at the level of the superior colliculus.


It has 2 adjacent nuclei:
  • oculomotor nucleus - somatic fibres (eye movements)
  • edinger-westphal nucleus - visceral fibres (pupillary constriction)

The oculomotor nerve passes between the posterior cerebral and superior cerebellar arteries, then on through the cavernous sinus and out through the superior orbital fissure.


In the orbit it splits into:
  • superior branch - supplies levator palpebrae
  • inferior branch - supplies medial rectus, inferior rectus and inferior oblique muscles and carries the visceral fibres

Complete 3rd nerve palsies tend to be peripheral rather than central in origin as the nucleus is big.


Classic 3rd nerve palsy:
  • ptosis
  • 'down and out' pupil
  • dilated pupil

If the pupil is spared it is sometimes referred to as a 'medical' third nerve palsy, whereas if it is fixed and dilated it is a 'surgical' third nerve palsy.

The reasoning behind this is that the visceral constrictive fibres run on the outside of the nerve so are spared in vascular aetiologies.


Causes of third nerve palsy:
  • diabetes (75% pupil-sparing)
  • temporal arteritis
  • SLE
  • MS
  • cavernous sinus thrombosis
  • amyloid
  • posterior communicating artery aneurysm (usually painful)
  • tumour


Webers syndrome: ipsilateral third nerve palsy with contralateral hemiplegia --> signifies a midbrain stroke.


After that pleasant forray into the world of neurology on to something completely different - G6PD deficiency...

MRCP revision battle 28.4: G6PD deficiency

Glucose-6-phosphate dehydrogenase deficiency is the commonest RBC enzyme defect.

It is x-linked recessive.


It causes intravascular haemolysis.


Generally patients are asymptomatic unless a crisis is precipitated, in which case they become anaemic and jaundiced.

Precipitants of crisis include:
  • drugs
    • primaquine
    • sulfonamides
    • ciprofloxacin
    • aspirin
  • broad/fava beans
  • illness


During a crisis a blood film will show:
  • bite cells
  • heinz bodies (=inclusions within RBCs of denatured haemoglobin)
 click here for a whole page of images of Heinz bodies


 Management is to avoid precipitants and transfuse if necessary.


On to Kaposi's sarcoma...

MRCP revision battle 28.5: Kaposi's sarcoma

Kaposi's sarcoma is a red, brown, purple or blue plaque on the skin or mucosa


Kaposi's sarcoma is derived from capillary endothelial cells or fibrous tissue.


It is associated with HHV-8.


It may be secondary to immunosupression, or a diagnosing feature of HIV infection.


Next up - CML....

MRCP revision battle 28.6: Chronic Myeloid leukaemia

Chronic myeloid leukaemia is an uncontrolled clonal proliferation of myeloid cells.

It tends to affect middle aged people (40 to 60 years)


Classical presentation is with:
  • decreased weight
  • tiredness
  • sweating

Possible additional presentations are:
  • gout due to increased purine breakdown
  • abdo pain due to splenomegaly
  • bleeding due to platelet dysfunction

Approximately 30% are detected by chance.


Features include:
  • elevated WCC - often 100-500
  • massive neutrophilia with left shift
  • low neutrophil alkaline phosphatase
  • splenomegaly in >75%


The philadelphia chromosome is present in >80% of cases

The philadelphia chromosome:
  • is a hybrid chromosome formed by t(9;22)
  • forms a gene BCR-ABL which results in excess tyrosine kinase activity
  • found in 80% CML, 5% children with ALL, 25% of adult ALL and 1% adult AML.
  • is associated with a good prognosis in CML but a poor prognosis in all other leukaemias


Treatment for CML is:
  • hydroxyurea
  • imatimib = glivec = specific BCR-ABL tyrosine kinase inhibitor
  • bone marrow transplant


CML transforms to AML in 80% of cases and ALL in 20%


Last battle of the day is Gertmann's Syndrome...

MRCP revision battle 28.7: Gerstmann's Syndrome

Gerstmann's Syndrome is a condition characteristed by:
  1. dysgraphia
  2. dyscalculia
  3. finger agnosia
  4. left-right disorientation

Gerstmann's Syndrome is associated with lesions in the dominant brain hemisphere in the region of the angular gyrus of the parietal lobe.


On that esoteric note, see you tomorrow!

Friday, 8 October 2010

MRCP revision battle 27.1: Heparin induced thrombocytopenia (HIT)

Today we have an epic set of battles with some real hard-hitters hidden amongst them, including sarcoidosis which is a differential for around 110% of MRCP questions (or at least thats what it feels like)   But if you get to the last battle you will be rewarded with lots of pictures (the joys of poikilocytosis) and then a link to look at some interesting non-medical pictures...


So the carrot is dangled, and here are the sticks:

MRCP revision battle 27.1: Heparin induced thrombocytopenia (HIT)
MRCP revision battle 27.2: Sarcoidosis
MRCP revision battle 27.3: Lofgren's syndrome
MRCP revision battle 27.4: Pancreatitis
MRCP revision battle 27.5: Visual field defects
MRCP revision battle 27.6: Paroxysmal nocturnal haemoglobinuria
MRCP revision battle 27.7: Poikilocytosis


MRCP revision battle 27.1: Heparin induced thrombocytopenia (HIT)

Heparin induced thrombocytopenia is one of those fabulous conditions whose name explains it all: low platelets, caused by heparin.  It is often abbreviated to HIT, which confused me greatly when I first had a patient affected by it and my consultant declared "ah, he's got HIT" which made me wonder who he was suspecting of abuse on the ward...


Technically there are 2 types of HIT:
  • Type 1 - occurs in first 2 days, is non-immune and the platelet count spontaneously recovers 
  • Type 2 - occurs 4 to 10 days after starting heparin, is immune-mediated and potentially life-threatening.

However, when HIT is mentioned, people generally mean type 2.


HIT is caused by antibodies against the heparin-platelet factor 4 complex.  These antibodies can be found in 90% of patients with HIT... but may also be present in unaffected patients taking heparin.


Ironically, although HIT is characterised by low platelets it is an incredibly pro-thrombotic condition.  As a result patients are likely to get PEs/DVTs and warfarin must absolutely not be started (since warfarin is initially prothrombotic too).  As you can see HIT causes something of a management problem - thrombosis due to the treatment you would give for thrombosis...


Management of HIT will involve specialist haematological input but in terms of MRCP question answers think:
  • stop heparin
  • stop/reverse warfarin
  • give lepirudin (=highly specific direct inhibitor of thrombin)


Note that HIT is more likely with unfractionated than LMW heparin.


Onwards to sarcoidosis...

MRCP revision battle 27.2: Sarcoidosis

Sarcoidosis is a multi-system granulomatous disorder of unknown cause.


It is asymptomatic in up to 40% of cases, being discovered incidentally on a routine CXR.


Features of sarcoidosis may be divided into pulmonary and non-pulmonary:

Pulmonary features of sarcoidosis:
  • dry cough
  • progressive dyspnoea
  • chest pain

Non-pulmonary features of sarcoidosis include:
  • lymphadenopathy (commonest in non-whites)
  • erythema nodosum (commonest in white females)
  • polyarthralgia
  • hepatomegaly
  • splenomegaly (around 25%)
  • anterior uveitis (around 25%)
  • glaucoma
  • Bells palsy
  • lupus pernio
  • hypercalcaemia
  • renal stones
  • pituitary dysfunction
  • cardiomyopathy...


90% of patients with sarcoid will have an abnormal CXR.
Staging of CXR in sarcoid is:
  • 0 = clear CXR
  • 1 = bilateral hilar lymphadenopathy
  • 2 = bilateral hilar lymphadenopathy plus pulmonary infiltration
  • 3 = pulmonary infiltration only
  • 4 = fibrosis, honeycombing, pleural involvement


Investigations:
  • raised ESR
  • lymphopenia
  • raised LFTs
  • raised serum ACE
  • raised calcium (5%)
  • tuberculin skin test is positive in around a third

Management:
  • BHL alone doesn't need treatment
  • acute sarcoidosis : NSAIDs and bed rest
  • prednisolone ( 40mg OD for 4-6 weeks then reducing dose over one year) is indicated if:
    • parachymal lung disease
    • uveitis
    • hypercalcaemia
    • neurological/cardiac involvement

Lets move on to briefly consider lofgrens syndrome...

MRCP revision battle 27.3: Lofgren's syndrome

Lofgrens syndrome is a subtype of sarcoidosis, characterised by:
  • erythema nodosum
  • bilateral hilar lymphadenopathy
  • fever
  • athralgia

It affects females more than males (85:15)


It carries a good prognosis - unlike sarcoidosis is unlikely to become chronic and most cases resolve in 6 months to 2 years.


On to something which often doesn't have a good prognosis... pancreatitis...

MRCP revision battle 27.4: Pancreatitis

Acute pancreatitis tends to present as epigastric/central abdominal pain radiating to the back with vomiting.  The pain may be improved by sitting forward.

Signs may be few; periumbilical discoloration (Cullen's sign) or flank discoloration (Grey Turner's sign) are rare.


Causes of pancreatitis can be remembered by I GET SMASHED:
  • idiopathic
  • gallstones
  • ethanol
  • trauma
  • steroids
  • mump
  • autoimmune
  • scorpion venom
  • hyperlipidaemia, hypercalcaemia, hypothermia
  • ERCP
  • drugs (steroids, ocreotide, sulphonamides, tetracyclines, azathioprine, sodium valproate)

Investigations:
  • bloods including amylase 
    • note amylase normalises in 24-48hrs; serum lipase is more sensitive and specific
  • AXR: ?sentinel loop ?loss of psoas shadow
  • CT abdo is the investigation of choice
  • score using the Modified Glasgow criteria.

Modified Glasgow criteria (helpfully spells out 'pancreas'):
  • Pa O2 <8
  • Age >55
  • Neurophils: WCC >15
  • Calcium: <2
  • Renal function: urea >16
  • enzymes: LDH >600; AST >200
  • Albumin: <32
  • Sugars: glucose >10
3 or more suggests severe pancreatitis.


Management of acute pancreatitis is:
  • lots of IV fluid, catheter for fluid balance
  • analgesia
  • close observation
  • treat cause

Complications of pancreatitis include:
  • early
    • sepsis
    • shock
    • ARDS
    • renal failure
    • DIC
    • hypocalcaemia
    • hyperglycaemia - 5% need insulin
  • late
    • necrosis and pseudocyst (=fluid in lesser sac)
    • abscess
    • fistulae
    • chronic pancreatitis


Now for something completely different, visual field defects...