Saturday, 13 November 2010

MRCP revision battle 48.1: Genital warts

Today's battles have a distinctly dermatological flavour to them...

MRCP revision battle 48.1: Genital warts
MRCP revision battle 48.2: Livedo reticularis and erythema ab igne
MRCP revision battle 48.3: Antiphospholipid syndrome
MRCP revision battle 48.4: Skin conditions associated with malignancy
MRCP revision battle 48.5: Sturge-Weber Syndrome
MRCP revision battle 48.6: Erythema multiforme
MRCP revision battle 48.7:  Toxic Epidermal Necrolysis and Steven-Johnson Syndrome


MRCP revision battle 48.1: Genital warts


Genital warts are not a topic I want to dwell on so lets make this very concise.


Posh medical name for genital warts = condylomata accuminata

Cause:
HPV, most commonly strains HPV 6 and HPV 11.
Less than 1% of people who become infected with HPV develop warts.


Prevention: gardasil vaccine protects against HPV 6 and 11 (associated with warts) and 16 and 18 (associated with cervical cancer)


Treatment:
  • 1st line: topical podophyllin/cryotherapy
  • 2nd line: imiquimod


Lets move rapidly onwards...

MRCP revision battle 48.2: livedo reticularis and erythema ab igne

livedo reticularis is a mottled, reticulated vascular pattern that appears like 'purple lace' on the skin.

Click here for an image
Click here for another


Causes of livedo reticularis include:
  • idiopathic - commonly occurs in young females
  • secondary
    • rheumatological: RA/SLE/PAN/dermatomyositis/antiphospholipid syndrome
    • pancreatitis
    • infections: TB/lyme disease/syphillis
    • lymphoma


Note how similar it looks to erythema ab igne (AKA livedo recticularis e calore) which is a rash caused by prolonged heat exposure, for example by sitting by a radiator or holding a hot water bottle.  (photo form wiki commons, taken by Dr Heilman)


Now lets move on to look at one of the causes of livedo reticularis, antiphospholipid syndrome

MRCP revision battle 48.3: Antiphospholipid syndrome

Antiphospholipid syndrome is characterised by:
  • recurrent venous/arterial thromboses
  • fetal loss
  • thrombocytopenia

Livedo reticularis may also be a feature.


Antiphospholipid syndrome is associated with:
  • lupus anticoagulant - an inhibitor of the coagulation pathway in vitro; pro-coagulant in vivo
  • anti cardiolipin antibodies - IgG and IgM

Management is with aspirin post thrombus, or if recurrent thromboses despite aspirin warfarin.

In pregnancy expert advice is needed; in general aspirin is taken once pregnant and LMWH started once the fetal heart is seen.  This is continued until 34 weeks.   This regime results in 70% success compared with 10% with nothing.


Now for some pictures...

MRCP revision battle 48.4: Skin conditions associated with malignancy

A brief run-through of a few skin conditions that can be associated with malignancy.

1.  Acanthosis nigricans

Acanthosis nigricans is a brown, velvety pigmentation of the skin, as illustrated below.


Acanthosis nigricans is associated with:
  • insulin resistance 
    • diabetes
    • acromegaly
    • cushings
    • obesity
    • hypothyroidism
  • PCOS
  • adenocarcinoma - particularly of GI tract/stomach


2. Acanthosis palmaris

Acanthosis palmaris, also known as 'tripe palms' is associated with lung or GI cancer.


3. Erythema gyratum repens

Erthema gyratum repens can be just the most beautiful swirly patterned erythema - click here to see a picture.  Unfortunately it is associated with lung cancer.


4. Necrolytic migratory erythema

From a beautiful rash to a truelly ugly one - necrolytic migratory erythema is associated with glucagonomas.  Click here for more information and images.


5. Sweets syndrome

These are tender purple-red plaques associated with haematological malignancy and IBD.  The patient is likely to have a fever.  The picture below is from wiki commons, posted by Cohen:


On to a very brief battle, Sturge-Weber syndrome...

MRCP revision battle 48.5: Sturge-Weber Syndrome

Sturge-Weber syndrome is the association of a port wine stain on the face with ipsilateral vascular  malformations and epilepsy.


Glaucoma and learning difficulties may also be features.


Now for some target lesions...

MRCP revision battle 48.6: Erythema multiforme

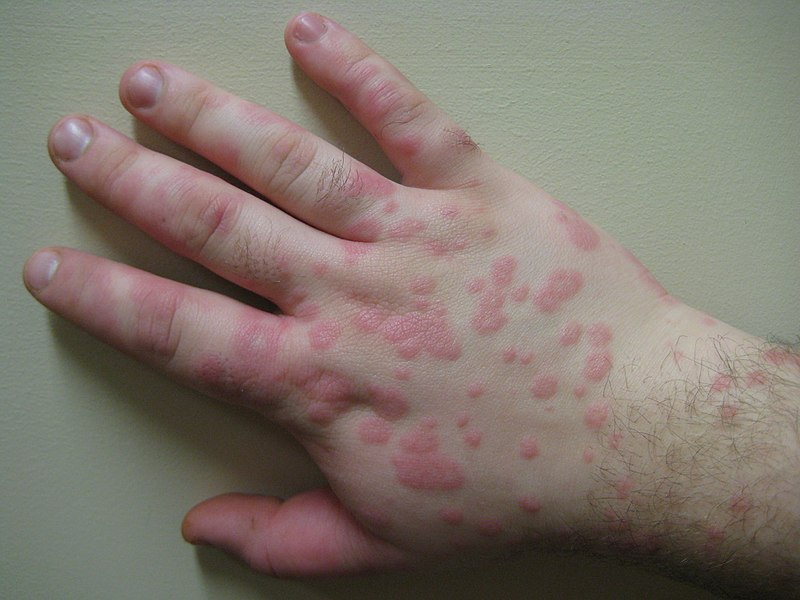
Erythema multiforme is characterised by target lesions.

Two pictures of erythema multuforme are below; the second is by Dr Heilmann.


50% of cases of erythema multiforme are idiopathic.

Secondary causes include:
  • drugs
    • penicillin
    • sulphonamides
    • phenytoin
    • carbamazepine
    • ACE-i
    • barbituates
    • NSAIDs
    • thiazides
  • infections
    • mycoplasma
    • herpes
    • orf

Management is to treat the underlying cause and supportive treatment.


For the final battle of the day on to what used to be considered as a severe form of erythema multiforme....

MRCP revision battle 48.7: Toxic Epidermal Necrolysis and Steven-Johnson Syndrome

Steven-Johnson Syndrome and Toxic Epidermal Necrolysis (TEN) are now consider to be varients of the same entity, with TEN being more severe.


They are characterised by irregular purpuric macules with occasional blistering and most patients also have extensive mucosal involvement. 

Although the appearence may initially seem similar to erythema multiforme (ableit more severe) histologically they are different:
  • erythema multiforme - cell-rich infiltrate, lots of T lymphocytes
  • SJS/TEN - cell-poor infiltrate, macrophages and dendrocytes

The difference between SJS and TEN is arbitrarily defined as SJS involves <10% body surface while TEN involves >30%.


The commonest cause of SJS/TEN is medication, with sulphonamides being the most commonly implicated drug.  

Other drug precipitants include:
  • phenytoin
  • carbamazepine
  • barbituates
  • allopurinol
  • penicillin
  • NSAIDs

The commonest time for SJS/TEN to develop is 9 to 14 days after starting a new drug.

Infections can also cause SJS/TEN.


In addition to the rash patients are systemically unwell and have a + Nikolsky's sign.


Management is:
  • stop precipitating drug
  • often ITU
  • IV IG
  • ?immunosupression ?plasmophoresis

Friday, 12 November 2010

MRCP revision battle 47.1: Membranous glomerulonephritis

A final assault on renal medicine!

MRCP revision battle 47.1: Membranous glomerulonephritis
MRCP revision battle 47.2: Diffuse proliferative glomerulonephritis
MRCP revision battle 47.3: Acute interstitial nephritis
MRCP revision battle 47.4: Chronic interstitial nephritis
MRCP revision battle 47.5: Alport's syndrome
MRCP revision battle 47.6: Renal papillary necrosis
MRCP revision battle 47.7: Mesangiocapillary glomerulonephritis


MRCP revision battle 47.1: Membranous glomerulonephritis


Membranous glomerulonephritis is the commonest cause of nephrotic syndrome in adults, accounting for around 30% of cases.

Peaks in incidence of membranous glomerulonephritis occur in the 2nd and 6th decade of life.


The key feature is IgG and C3 on the basemement membrane

The complication to be aware of is renal vein thrombosis which occurs in 5% of cases.


Secondary causes of membranous glomerulonephritis include:
  • malignancy
  • connective tissue disease: RA/SLE/sjogrens
  • infection: HBV/HCV/malaria/syphilis
  • drugs: NSAIDs/gold/penicillamine/captopril
  • other: GBS/sarcoid


In terms of prognosis 1/3 recover spontaneously, 1/3 recover after treatment with immunosupression and 1/3 develop renal failure.


Now on to another glomerulonephritis...

MRCP revision battle 47.2: Diffuse proliferative glomerulonephritis


Diffuse proliferative glomerulonephritis classically presents after a streptococcal infection or impetigo.  It tends to affect children and young adults.


Diffuse proliferative glomerulonephritis tends to cause nephritic syndrome or acute renal failure.


Immunofluorescence shows C3 and IgG.
Serology shows decreased C3 and raised ASOT


Treatment is supportive and >95% recover.


Now lets consider nephritis...

MRCP revision battle 47.3: Acute Interstitial Nephritis

Interstitial nephritis is inflammation of the renal interstitium.


Acute interstitial nephritis

This is an immune reaction to drugs or infection.
It accounts for 2% of all acute renal failure but 25% of drug-induced renal failure.


Features include:
  • acute renal failure
  • hypertension
  • systemic symptoms
    • rash
    • fever
    • eosinophilia, raised IgE

>1% urinary eosinophils suggests diagnosis


Renal biopsy would show infiltration of the renal interstitium with:
  • T lymphocytes
  • macrophages
  • plasma cells

Causes include:
  • infections: hanta virus, leptospirosis, mycobacterium, staph, strep
  • drugs: methicillin, NSAIDs, rifampacin, allopurinol, penicillin, cephalosporins, furosemide, thiazides, amphotericin, aspirin
  • sarcoid

Lets move on to consider a hat-trick of causes of chronic interstitial nephritis

MRCP revision battle 47.4: Chronic interstitial nephritis

Chronic interstitial nephritis/tubulointerstitial nephritis can be caused by many conditions and results in fibrosis and tubular loss which manifests clinically as chronic renal failure


Analgesic nephropathy

Analgesic nephropathy is associated with long-term use of NSAIDs, and to a lesser degree paracetamol.


It may present as:
  • sterile pyuria
  • chronic renal failure
  • renal pain (due to papillary necrosis)

An IVU will show 'cup and spill' calyces
Renal biopsy may show interstitial nephritis

Treatment is to stop the analgesics and managed any renal failure.


There is an increased risk of urothelial tumours.


Reflux Nephropathy

Reflux nephropathy is defined as small and irregularly scarred kidneys associated with vesico-ureteric reflux.

Almost always only occurs in first 5 yrs of life.

Associated with an increased risk of renal stones.


Balkan Nephropathy

Balkan nephropathy is a chronic interstitial renal disease found in a distribution along the River Danube.

It is associated with coppery yellow pigmentation of palms and soles.
There is raised beta 2 microglobinuria.

Urothelial malignancy is much increased - up to 200x risk.


Now on to Alport's syndrome...

MRCP revision battle 47.5: Alport's syndrome

Alport's syndrome is an inherited kidney disease with an incidence of 1 in 5000.

It is inherited in an X-linked dominant fashion 85% of the time; 15% are autosomal recessive.


Alport's is an abnormality in the gene that codes for type IV collagen.


It is associated with:
  • abnormal GBM - 'basket weave' --> chronic renal failure, 30% nephrotic
  • sensorineural deafness
  • occular defects in 40%
    • lenticonus = bulging lens capsule on slit lamp exam
    • retinitis pigmentosa

Treatment is treating symptoms.

Onwards...

MRCP revision battle 47.6: Renal papillary necrosis

Renal papillary necrosis is a form of nephropathy involving the renal papilla (= location where medullary pyramids empty urine into minor calyx)


It can cause pain and a sterile pyuria.


An IVU may show 'cup and spill' calyces.


Causes of renal papillary necrosis may be recalled as 'POSTCARDS'
  • pyelonephritis
  • obstruction of renal tract
  • shock
  • TB
  • cirrhosis of liver
  • analgesic nephropathy
  • renal transplant rejection
  • diabetes
  • sickle cell


On to the final battle of the day, mesangiocapillary glomerulonephritis...

MRCP revision battle 47.7: Mesangiocapillary glomerulonephritis

Mesangiocapillary glomerulonephritis, also known as membranoproliferative glomerulonephritis is a rare form of glomerulonephritis.


There are 3 subtypes:


Type 1:
  • subendothelial immune deposits
  • caused by cryoglobulinaemia, hepatitis C
  • also associated with:
    • hep B
    • bacterial endocarditis
    • SLE
    • malaria
    • sickle cell disease
Type 2:
  • intramembranous electron-dense material --> 'double tramline'
  • associated with partial lipodystrophy
  • C3b nephritic factor present in 70%
  • low C3

Type 3:
  • associated with hepatitis B and C

Treatment is with steroids

50% of patients progress to end stage renal failure.

Thursday, 11 November 2010

MRCP revision battle 46.1: Classification of bacteria

A completely random mixed bag today, bursting full of random nuggets of MRCP knowledge...


MRCP revision battle 46.1: Classification of bacteria
MRCP revision battle 46.2: Tumour supressor genes and Li Fraumeni Syndrome
MRCP revision battle 46.3: Mitochondrial disorders and Leber's Optic Atrophy
MRCP revision battle 46.4: Cytotoxic Agents
MRCP revision battle 46.5: Congenital infections
MRCP revision battle 46.6: Rheumatoid factor
MRCP revision battle 46.7: Lichen Planus


MRCP revision battle 45.1: Classification of bacteria


MRCP questions just love commenting on the colour/shape of bacteria.  Hopefully my simple picture below (which was also stuck next to the loo during finals!) might help you.  Note that gram positive bacteria have walls so stain purple/blue while gram negative bacteria don't and stain pink.


My way of remembering them is 'SES ('says') ABCD then L....MN then all the rest'


As well as their colour/shape their 'pattern' is useful to know too:
  • pairs of cocci (= diplococci): neisseria gonorrhoea, neisseria meningitidis
  • chains of cocci: streptococci, enterococci
  • clumps of cocci: staphylococci


Now for some genetics...

MRCP revision battle 46.2: Tumour supressor genes and Li Fraumeni Syndrome

Tumour supressor genes code for proteins that provide a 'stop' signal to prevent cell division.  They therefore act as a barrier to the development of cancer.  As they are recessive genes both copies of the gene would have to be mutated to stop functioning.


The most famous tumour supressor gene is p53.

p53 is:
  • found on chromosome 17
  • the most commonly mutated gene in breast, colon and lung cancer
  • a key regulator of apoptosis and prevents entry into the S phase of the cell cycle until the DNA is checked.


Li Fraumeni Syndrome is a rare condition in which there is an autosomal dominant p53 mutation.  More rarely it may be caused by a CHEK-2 mutation. Li Fraumeni syndrome is characterised by early onset of cancer, especially breast, sarcoma or soft tissue.  


Lets move on to mitochondrial disorders...

MRCP revision battle 46.3: Mitochondrial disorders and Leber's Optic Atrophy

mDNA mutates 10x more frequently than normal DNA.  However, there is a poor genotype to phenotype correlation so the mutations are often not noticed.


Since sperm do not contain mitochondria mitochondrial disorders are passed exclusively from mother to child.


The most famous mitochondrial disorders are:

  1. Kearns Sayre - see battle 15.5
  2. Leber's hereditary optic neuropathy.
  3. Some forms of sensorineural deafness


Leber's hereditary optic neuropathy
  • mDNA mutation
  • progressive loss of central vision due to optic atrophy, begins in young adulthood
  • if LHON 'plus' also:
    • multiple-sclerosis type symptoms
    • Wolff-Parkinson White


Next up - some cytotoxic agents (which sadly sounds more exciting than it is)

MRCP revision battle 46.4: Cytotoxic Agents

A quick run-through of the main mechanisms of action and MRCP-relevant side-effects of some common cytotoxic agents.


Vincristine
  • Inhibits microtubule formation
  • Used in:
    • lyphoma
    • leukaemia
    • breast and lung cancer
  • Side effects
    • peripheral paraesthesia
    • loss of tendon reflexes
    • abdominal pain

Cisplatin
  • Cross-links DNA
  • Used in:
    • testicular, cervical, bladder, lung, head and neck cancers
  • Side effects
    • nephrotoxic
    • ototoxic
    • peripheral neuropathy
    • hypomagnesaemia
    • myelosupression


Bleomycin
  • Degrades DNA
  • Used in:
    • metastatic germ cell cancers
    • non-Hodgkins lymphoma
  • Side effects
    • increased pigmentation
    • pulmonary fibrosis


Doxorubicin
  • inhibits RNA/DNA synthesis
  • used in:
    • leukaemia
    • lyphoma
    • breast cancer
  • Side effects
    • red colouration of urine
    • SVT
    • cardiomyopathy

Methotrexate
  • inhibits dihydrofolate reductase
  • used in:
    • non-Hodkins lymphoma
    • choriocarcinoma
    • RA
  • Side effects
    • excreted by kidneys so should be avoided in renal disease
    • should be avoided in significant ascites/pleural effusion as may accumulate then suddenly return to circulation causing myelosupression
    • myelosupression
    • mucositis
    • pneumonitis


Cyclophosphamide
  • alkylating --> cross links DNA. Inactive until metabolised by liver
  • used in:
    • CLL
    • lymphoma
    • sarcoma
  • Side effects
    • haemorrhagic cystitis 


To continue the randomness of the 46th set of battles lets look at congential infections

MRCP revision battle 46.5: Congenital infections

A few short notes on 5 infections mummies may have during pregnancy which can adversely affect the fetus...


Maternal rubella
  • fetus is nearly always affected if rubella occurs during first 7 weeks of gestation
  • fetus is nearly always OK if rubella occurs after 17 weeks of gestation
  • Effects of rubella on fetus:
    • sensorineural deafness
    • congenital cateracts
    • congenital heart disease
    • glaucoma


Maternal toxoplasmosis
  • fetus will only be affected if it is the first time the mother is exposed, unless she is immunosupressed
  • classical triad is:
    • cerebral calcification
    • hydrocelphalus
    • chorioretinitis


Maternal chickenpox
  • if this occurs during the 1st trimester risk of limb deformity
  • if mum has been in contact with chickenpox and is not sure if she is immune test for antibodies and if no natural immunity give immunoglobulin


Maternal CMV
  • at least 75% of fetus' exposed to CMV are undamaged
  • however, there is a risk of:
    • intracranial calcification
    • microcephaly
    • cardiac/GI abnormalities

Maternal Parvovirus B19
  • generally either fetal death or complete recovery


Now for a spot of rheumatoid factor

MRCP revision battle 46.6: Rheumatoid factor

Rheumatoid factor is an autoantibody against the Fc portion of IgG.  

Rheumatoid factor is found in 4% of the 'normal' population and 25% of elderly.


Rheumatoid factor is positive in low titres in chronic infections, for example:
  • 10% syphyllis
  • 20% pulmonary TB
  • 50% leprosy


Rheumatoid factor is often positive in high titres in connective tissue disease, for example it is positive in:
  • 70% of patients with RA
  • virtually 100% of patients with RA with extra-articular manifestations
  • >75% sjogrens
  • 20-40% SLE
  • 30% scleroderma

It may also be present in other immunological diseases, for example autoimmune liver disease or sarcoidosis.


Very high titres of rheumatoid factor may be found in cryoglobulinaemias


Rheumatoid factor is only useful in RA as an assessment of prognosis.  It is not useful for diagosis or or measuring level of activity.


Rheumatoid factor is detected by the Rose-Waaler test (sheep red cell agglutination) or the latex agglutination test.


Now to the final battle of the day - lichen planus